


The disease begins with changes in the cartilage of the joints, causing the joint surfaces of the bones to slip.Malnutrition and loss of elasticity lead to its degeneration and absorption. At the same time, the bone tissue on the articular surface is exposed, sliding is damaged, the joint space narrows, and the joint biomechanics changes.The synovial membrane that covers the joints and produces synovial fluid (which nourishes the cartilage and acts as a physiological lubricant) becomes irritated, causing an increase in the amount of synovial fluid in the joint (synovitis).Against the background of narrowing of the joint space, the volume of the joint decreases, and synovial fluid protrudes into the posterior wall of the joint capsule, forming a Becker's cyst (when the cyst enlarges, it can cause pain in the popliteal fossa).

The thin, fragile tissue of the joint capsule is replaced by rough connective tissue, and the shape of the joint changes.Bone tissue grows around the joint, forming osteophytes (pathological bone growth).Blood circulation in periarticular tissues is disturbed, underoxidized metabolites accumulate in them, stimulate chemoreceptors, and a persistent pain syndrome occurs.Against the background of changes in the anatomy of the joint, the function of the surrounding muscles is disrupted, atrophy and spasticity occur, and gait is disturbed.A persistent limitation in the joint's range of motion (contracture), sometimes so pronounced that only rocking motion is possible (rigidity) or a complete lack of motion (rigidity).
Knee joint disease is a fairly common condition: it affects 10% of the planet's population, and one in three people over the age of 60.
Causes of knee joint disease
- Bone and joint injuries.
- Inflammatory joint diseases (rheumatoid, gout).
- Disorders of mineral metabolism in various endocrine diseases (diabetes, parathyroid disease, hemochromatosis).
- Disorders of the muscular system and neuropathy (Charcot's disease).
In addition to the main causes, there are some unfavorable background factors for the development of knee arthropathy, including:
- Being overweight (literally putting pressure on the lower body);
- Age (most older adults are affected by the disease);
- Women (statistically, women are more likely to get sick);
- Increase sports and professional sports activities.
Symptoms of knee osteoarthritis
- The pain increases with walking and decreases with rest.
- Difficulty in habitual physiological movements of joints.
- The characteristic "crunching" sound at the joints.
- Increased joint size and visible deformation.
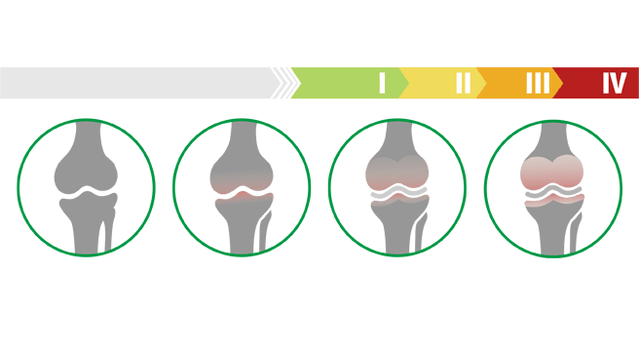
stages of knee joint disease
Clinical stages of knee arthritis.The disease goes through several stages.
- In the first stage, people will only feel a slight discomfort or "heaviness" in the knee, which can be disconcerting when walking long distances or increasing physical activity.X-rays provide no information: only a slight narrowing of the joint space and no other changes can be detected.At the onset of an illness, a person does not seek help from experts and does not pay much attention to the symptoms that arise.
- The second stage is characterized by pronounced pain, the severity of which decreases with rest.It is difficult to move the joints, and a characteristic "squeaking" sound can be heard when walking (a common saying in daily life can be heard from patients: "knee creaking").X-ray shows clearly visible joint space narrowing and isolated osteophytes.
- When knee arthrosis progresses to the next third stage, pain will continue to bother the patient, including at rest, and the joint structure will become deranged, that is, deformed, and swelling will increase during inflammation.Radiographs showed moderate narrowing of the joint space and multiple osteophytes.In the third stage, many people have sought medical help because... quality of life has significantly decreased due to pain and difficulty walking normally.
- Stage four is accompanied by constant, debilitating pain.For a person, the smallest attempt to move becomes an ordeal, joint deformations are visually apparent, and walking is extremely difficult.The X-ray showed significant changes: the joint space was barely defined in the image, showing multiple rough osteophytes, "joint mice" (degenerated bone fragments falling into the joint space).Knee arthrosis at this stage almost always results in disability: often the disease results in complete joint fusion, instability and the formation of "pseudarthrosis".
Who Treats Knee Arthritis?
Therapists, rheumatologists, and general practitioners (family doctors) can provide qualified medical care for patients with knee arthritis, but these specialists treat uncomplicated knees.When synovitis occurs or the treatment prescribed by the therapist does not have the desired effect, you cannot do without the help of an orthopedic surgeon.In cases where surgical treatment is required, patients are sent to specialized orthopedics and trauma units.
How and what is used to treat knee arthritis?
Currently known methods for treating knee arthritis are divided into non-drug conservative treatments, drug treatments and surgical treatments.
non-pharmacological methods
Many patients will ask: "How to treat knee arthritis without taking medicine?" When answering this question, we regret to point out that knee joint disease is a chronic disease and cannot be eliminated forever.However, many current non-drug approaches to combating the disease can significantly slow its progression and improve patients' quality of life, especially when used in the early stages of the disease.If treated promptly, the patient is sufficiently motivated to heal, which is sometimes enough to eliminate negative factors.For example, it has been shown that losing excess weight can reduce the manifestation of the main symptoms of the disease.
Elimination of pathological physical activities and, on the contrary, therapeutic exercises with a sound body plan can reduce the intensity of pain.Exercises to improve quadriceps strength have been shown to be as effective as anti-inflammatory medications.
If you are treating knee arthrosis, you must strive for proper nutrition: products containing a large amount of animal collagen and chondroitin (shrimp, crab, krill), fresh vegetables and fruits rich in plant collagen and antioxidants, can help improve the elasticity of joint cartilage, while eating bacon, pickles, preservatives, sweet and salty dishes will instead aggravate metabolic disorders in the body, accumulate overweight and lead to obesity.
When thinking about what are the most effective treatments for knee joints, it is worth remembering such effective therapeutic and preventive methods as orthotics: fixed knee braces, orthotics, elastic bandages and orthopedic insoles can reduce and correctly distribute the load on the joint, thereby reducing the intensity of joint pain.
Comprehensive treatment of knee arthritis also includes prescribed physical procedures that are very effective even in advanced forms of the disease.Magnetic therapy has proven its effectiveness when widely used in different categories of patients suffering from this disease: after several treatments, the intensity of pain decreases, swelling decreases due to improved blood circulation, muscle spasms disappear, and joint mobility increases.The effect of magnetic therapy is particularly pronounced when there is active inflammation of the joints: the severity of edema is significantly reduced, and the symptoms of synovitis subside.Physical treatments such as laser therapy and cryotherapy (cold exposure), although less popular, are equally effective in treating knee arthritis and have significant pain relief.
drug treatment
Nonsteroidal anti-inflammatory drugs (NSAIDs), available in both topical (various gels, ointments) and systemic (tablets, suppositories, solutions) forms, have long proven their effectiveness in treating osteoarthritis and are widely used by physicians.By blocking inflammation at the enzyme level, they can eliminate joint pain and swelling and slow the progression of the disease.For early manifestations of the disease, topical application of these agents in combination with nonpharmacological methods is effective.But for advanced knee osteoarthritis, you can't live without medication.It must be remembered that long-term systemic use of NSAIDs leads to the development and exacerbation of ulcerative processes in the gastrointestinal tract, in addition to negative effects on renal and liver function.Therefore, patients who take NSAIDs for a long time should also take drugs to protect the gastric mucosa and regularly monitor laboratory parameters of internal organ function.
In cases of advanced, "end-stage" osteoarthritis, when a person experiences excruciating pain that does not subside even at rest, disrupts normal sleep, and is not relieved by NSAIDs, corticosteroids, and nonpharmacological methods, opioid pain relievers may be prescribed.These medications should only be used with a doctor's prescription, and your doctor will consider prescribing recommendations on a case-by-case basis.
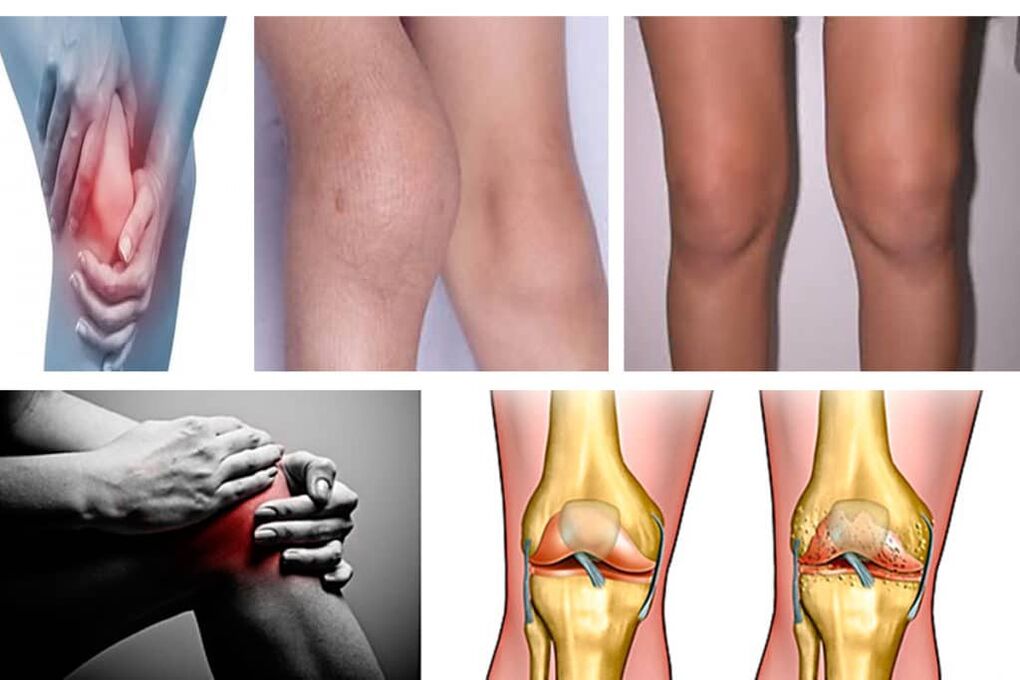
Chondroprotectant (literally "protecting cartilage").This name refers to a variety of drugs that possess a single property - structure-modifying effects, that is, the ability to slow degenerative changes in cartilage and narrowing of joint spaces.They are produced for oral administration (glucosamine, chondroitin sulfate, piascledin) and for injection into the joint space (hyaluronate).Of course, these drugs won't work miracles or "grow" new cartilage, but they can stop its destruction.To achieve lasting results, they must be used over the long term, several times a year during regular sessions.
Surgical treatment of knee arthritis
In many cases, despite adequate comprehensive treatment, the disease progresses, gradually reducing a person's quality of life.In this case, patients begin to ask questions: "What if the prescribed drugs do not help the knee joint?", "Does the knee joint require surgical treatment?", "How is the knee joint surgically treated?" When answering these questions, it needs to be clear that the indications for surgical treatment of knee osteoarthritis are intractable pain syndromes and significant joint dysfunction that cannot be eliminated by complex conservative treatments.
The most popular type of surgical treatment for knee osteoarthritis is endoprosthesis, in which one's own joint is removed and immediately replaced with a metal prosthesis designed to resemble the anatomy of the human knee joint.At the same time, the prerequisite for such surgical treatment is that there is no obvious deformity of the joint, the formation of "pseudoarthrosis", muscle contracture and obvious muscle atrophy.
In the case of severe osteoporosis (significant decrease in bone mineral density), the use of endoprostheses is also not necessary: the "sugar" bone cannot withstand the introduction of metal nails, the bone tissue will begin to resorb rapidly at the site of its installation, and pathological fractures may occur.Therefore, it is important to make a timely decision on whether to install an endoprosthesis - when the age and general condition of the person still permit surgery.According to the results of long-term studies, the duration of the effect of endoprostheses, i.e. the duration in which significant movement restrictions are temporarily eliminated and a good quality of life is maintained, is approximately ten years.The best results of surgical treatment are observed in people aged 45-75 years, with a low body weight (less than 70 kg) and a relatively high standard of living.
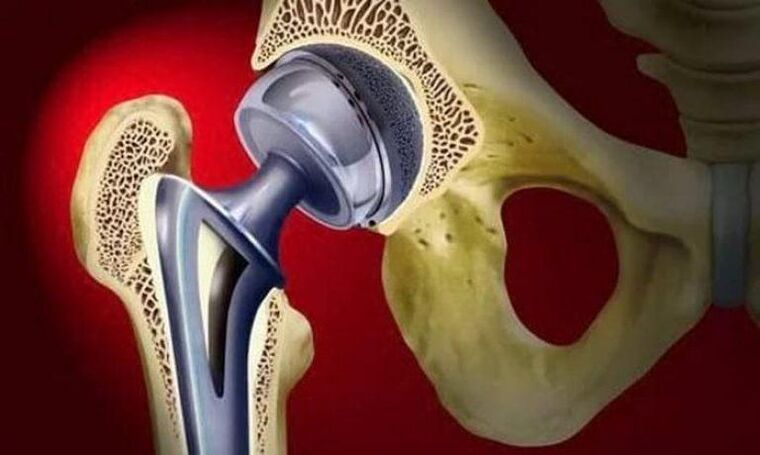
Despite the widespread use of knee replacement surgery, the outcomes of this type of surgery are often suboptimal and the complication rate is high.This is due to the design features of the endoprosthesis and the complexity of the surgical intervention itself (hip replacement is technically much simpler).These include medullary bypass surgery and corrective osteotomies.An articular medullary shunt uses a shunt (a hollow metal tube) to connect the femoral medullary canal to the knee joint cavity.As a result, fatty marrow from the lower third of the femur enters the knee joint, nourishes and lubricates the cartilage, thereby significantly reducing pain.
When the axis of the lower limb changes (but the range of motion is slightly limited), corrective osteotomy is effective - the tibia is crossed and its axis is corrected, then fixed in the desired position with plates and screws.In this case, two goals are achieved - normalization of biomechanics due to restoration of the limb axis, and activation of blood circulation and metabolism during bone fusion.Although today's medicine cannot provide a permanent cure for this disease with drugs or other methods, a healthy lifestyle, seeking prompt medical help, and following your doctor's advice can halt its progression.